 Medication Administration and CompetencyHalloween offerBuy one licence, get the second free: £12.99 each · ends 31 OctAdd to basket
- 8lessons
- 1 hourto complete
- 1CPD hours
- October 2026last updated
When you need this course
- Your yearly competency check is dueThe knowledge online in about 1 hour, then you observe each carer in practice and sign them off.
- There has been a medication errorCovers errors, the limits of a carer’s role and when to seek advice.
- Someone lacks capacity or refuses medicinesIncludes consent, capacity and covert medication, done the right way.
- CQC asks about your medicines trainingEvery learner gets a dated, CPD Certified certificate once you have signed off their practical.
Try it: a real lesson and question from this course

The law, guidance and your role
Medicines help people live well, but used incorrectly they cause serious harm. Several laws apply. The Human Medicines Regulations 2012 control how medicines are made, supplied and prescribed. The Misuse of Drugs Act 1971 and the Misuse of Drugs Regulations 2001 control controlled drugs, such as morphine and fentanyl, including how they are stored and recorded. The Health and Social Care Act 2008 (Regulated Activities) Regulations 2014 require the proper and safe management of medicines (Regulation 12), which the Care Quality Commission inspects. The Mental Capacity Act 2005 applies to consent.
National guidance sets out good practice: NICE SC1, managing medicines in care settings, and NICE NG67, managing medicines for adults receiving social care in the community. CQC publishes detailed medicines guidance for care settings, home care and supported living. Your employer's medicines policy turns all of this into the procedures you follow, and you must know it.
Everyone has a role. The prescriber, usually the GP or a nurse or pharmacist prescriber, decides what the person needs and writes the prescription. The pharmacist dispenses it, labels it, and gives advice. Your employer provides the policy, training and assessment of competence and keeps records. You administer or support people with medicines only as trained, assessed and authorised, following the prescription, label and MAR, and you observe and report. The person has the right to be involved, to be informed and to refuse.
There are different levels of support. Some people manage their own medicines, sometimes with prompting or reminders. Others need assistance, such as opening packaging. Some need medicines administered: selecting, preparing and giving the medicine. The person's care plan and medicines risk assessment say which applies, and it should be reviewed when their needs change. People who can manage their own medicines should be supported to keep doing so.
Which regulations control how controlled drugs are stored and recorded?
In the hub, a wrong answer sends the staff member a short follow-up lesson and a fresh question on the same point. They close the gap before they can finish the module, and every attempt is recorded for your CQC evidence.
Next: one of the course's interactive activities, exactly as your staff get it.
Try it yourself
CareStream InteractiveWho does what?
Match each role to its responsibility.
Tap a term on the left, then its meaning on the right
Term
Meaning
This exercise is here to help you practise — it is not marked and does not affect your result.
That is how the training works. Give your whole team the full Medication Administration and Competency module.



What the course covers: 8 lessons
- The law, guidance and your role
- Common medicines and their use
- Consent, capacity and covert medication
- Preparing to administer
- Administration techniques
- Recording and monitoring
- Controlled drugs, storage and disposal
- Errors, your limits and seeking advice
Assessment and certificate
- 32 question assessment with a pass mark of 80%.
- A follow-up lesson on anything a learner gets wrong, so the gaps are closed, not just scored.
- A named, dated certificate the moment they pass, carrying the CPD Certified mark and CPD hours, ready to download as a PDF.
- Kept on their training record in your dashboard, ready for your CQC evidence.
- An observation checklist for the observed workplace assessment the employer carries out.
Free Medication Administration and Competency resources
Official guidance from Skills for Care, free to download. Useful alongside the course.
- Skills for Care: statutory and mandatory training guideWhat Skills for Care expect every course on this subject to cover, and how often.
- NICE SC1: managing medicines in care homesNICE guidance for care homes on managing medicines.
- NICE NG67: managing medicines for adults receiving social care in the communityNICE guidance for home care services.
Specialists in the technology behind it all
The same technology behind the world's best products powers CareStream, so your team's medication administration and competency training stays accurate, always up to date with the latest guidance, and is delivered in over 60 languages.
Avg. Duration
About 1 hour
Certificate
For every staff member
Available Languages (60+)
CPD Certified Course
A clear, practical grounding in medication administration and competency.
Eight short lessons, each with a care scenario, an interactive activity and a quick check with an explanation. You start with a five question knowledge check, then finish with a 32 question assessment with a pass mark of 80%. Your manager or a suitably trained assessor then observes a medicines round against a 12 point checklist; every point must be met before your certificate is issued.
By the end, your staff will be able to:
- Explain the law, national guidance and policies that apply to medicines in social care, and the roles of everyone involved
- Describe common types of medicines, what they are used for and the side effects to look out for
- Apply the principles of consent and mental capacity, including when a person refuses and when covert administration is considered
- Prepare for and administer medicines safely using the six rights, by the correct route and technique
- Record administration accurately, monitor the person's response and handle controlled drugs and storage correctly
- Recognise medication errors and near misses, act on them immediately, and know the limits of your role
A closer look at the medication administration and competency module.
The module is built in short, practical sections. Each one teaches a part of the topic, then applies it to a real care scenario and checks understanding before moving on.
The law, guidance and your role
Medicines help people live well, but used incorrectly they cause serious harm. Several laws apply. The Human Medicines Regulations 2012 control how medicines are made, supplied and prescribed. The Misuse of Drugs Act 1971 and the Misuse of Drugs Regulations 2001 control controlled drugs, such as morphine and fentanyl, including how they are stored and recorded. The Health and Social Care Act 2008 (Regulated Activities) Regulations 2014 require the proper and safe management of medicines (Regulation 12), which the Care Quality Commission inspects. The Mental Capacity Act 2005 applies to consent. National guidance sets out good practice: NICE SC1, managing medicines in care settings, and NICE NG67, managing medicines for adults receiving social care in the community. CQC publishes detailed medicines guidance for care settings, home care and supported living. Your employer's medicines policy turns all of this into the procedures you follow, and you must know it. Everyone has a role. The prescriber, usually the GP or a nurse or pharmacist prescriber, decides what the person needs and writes the prescription. The pharmacist dispenses it, labels it, and gives advice. Your employer provides the policy, training and assessment of competence and keeps records. You administer or support people with medicines only as trained, assessed and authorised, following the prescription, label and MAR, and you observe and report. The person has the right to be involved, to be informed and to refuse. There are different levels of support. Some people manage their own medicines, sometimes with prompting or reminders. Others need assistance, such as opening packaging. Some need medicines administered: selecting, preparing and giving the medicine. The person's care plan and medicines risk assessment say which applies, and it should be reviewed when their needs change. People who can manage their own medicines should be supported to keep doing so.
Common medicines and their use
Knowing what a medicine is for helps you give it safely and notice problems. Common groups include pain relief, such as paracetamol and opioids like codeine and morphine; antibiotics for infections; anticoagulants, which thin the blood, such as warfarin, apixaban and rivaroxaban; medicines for the heart and blood pressure; diuretics, sometimes called water tablets; medicines for diabetes, including insulin; inhalers for asthma and COPD; laxatives; and medicines for mental health, epilepsy, Parkinson's disease and dementia. Medicines come in many forms: tablets and capsules, some designed to dissolve slowly (modified or slow release); liquids; creams and ointments; patches; inhalers; eye, ear and nose drops; suppositories; and injections. The form matters: it affects how the medicine works and how it must be given. Some medicines are high risk, because small mistakes can cause serious harm. They include anticoagulants, insulin, opioids, methotrexate (usually taken once a week, not daily), and medicines for epilepsy and Parkinson's disease. Some medicines are time critical: for example, Parkinson's medicines must be given at the exact times prescribed, because delays can quickly cause stiffness, falls and swallowing problems. All medicines can cause side effects. Common ones include drowsiness, dizziness, falls, constipation, nausea, confusion and rashes. Anticoagulants can cause bleeding and bruising. Report anything new or unusual after a medicine is started or changed. A severe allergic reaction, with swelling of the face or throat or difficulty breathing, is an emergency: call 999. Homely remedies are non prescription medicines, such as paracetamol for a headache, that a care setting may give under a policy agreed with the GP or pharmacist. Only give them as the policy allows, and check they will not interact with the person's prescribed medicines or duplicate them.
Consent, capacity and covert medication
People have the right to make decisions about their own medicines, including the right to refuse. Always explain what the medicine is, what it is for, and gain the person's consent before giving it. The Mental Capacity Act 2005 says a person must be assumed to have capacity unless it is established that they lack it for that specific decision, and they must be supported to decide, for example by explaining simply, using pictures or choosing a better time. If a person with capacity refuses a medicine, respect their decision. Do not force or trick them. You may gently offer it again a little later, or find out why, such as difficulty swallowing, side effects or a misunderstanding. Record the refusal on the MAR with the correct code, and report it, particularly for important medicines such as antibiotics, anticoagulants or insulin, so the prescriber can be told. Repeated refusals need a review. Covert administration means giving a medicine hidden in food or drink so the person does not know. It is only ever considered for a person who lacks capacity to make the decision about their medicine, when it is essential to their health. It must follow a best interests decision involving the prescriber, a pharmacist, care staff and the person's family or representative, and be recorded in a covert medicines plan. A pharmacist must advise how each medicine can be given, because crushing tablets or mixing medicines with food can make them unsafe or ineffective; crushing a slow release tablet, for example, can release the whole dose at once and cause an overdose. Covert administration must be used for as short a time as possible and reviewed regularly. You must never decide to give medicine covertly yourself. Restraint to give medicines is not acceptable except in exceptional, legally authorised circumstances. If you are unsure whether a person can consent, ask the senior.
Preparing to administer
Safe administration starts with preparation. Wash your hands. Work in a clean, well lit area, and avoid interruptions: many services use a "do not disturb" tabard during medicines rounds, because interruptions cause errors. Have the MAR, the medicines, the person's care plan, water and any equipment ready. Use the six rights for every medicine. Right person: confirm who the person is, for example by their photograph on the MAR, asking their name and date of birth if they can tell you, and checking with colleagues who know them. Never rely on room numbers alone. Right medicine: check the pharmacy label against the MAR, including the name and strength. Right dose: check the amount and how much is left. Right route: by mouth, on the skin, into the eye, and so on. Right time: check when it is due and when any previous dose was given, including for when required medicines. Right documentation: record it straight away. Many services add the right to refuse. Also check allergies, recorded on the MAR and care plan, and any special instructions on the label, such as "take with or after food", "swallow whole" or "take 30 minutes before breakfast". Check the expiry date, and that liquids, creams and eye drops have not passed their use by date once opened, which should be written on them. Stop and get advice if anything does not match: the label and MAR differ, a dose looks unusual, the medicine looks different from usual, or the MAR is unclear or handwritten without being checked. Never guess, and never use medicines prescribed for someone else. Monitored dosage systems, such as blister packs, help, but do not remove the need to check each medicine against the MAR.
Administration techniques
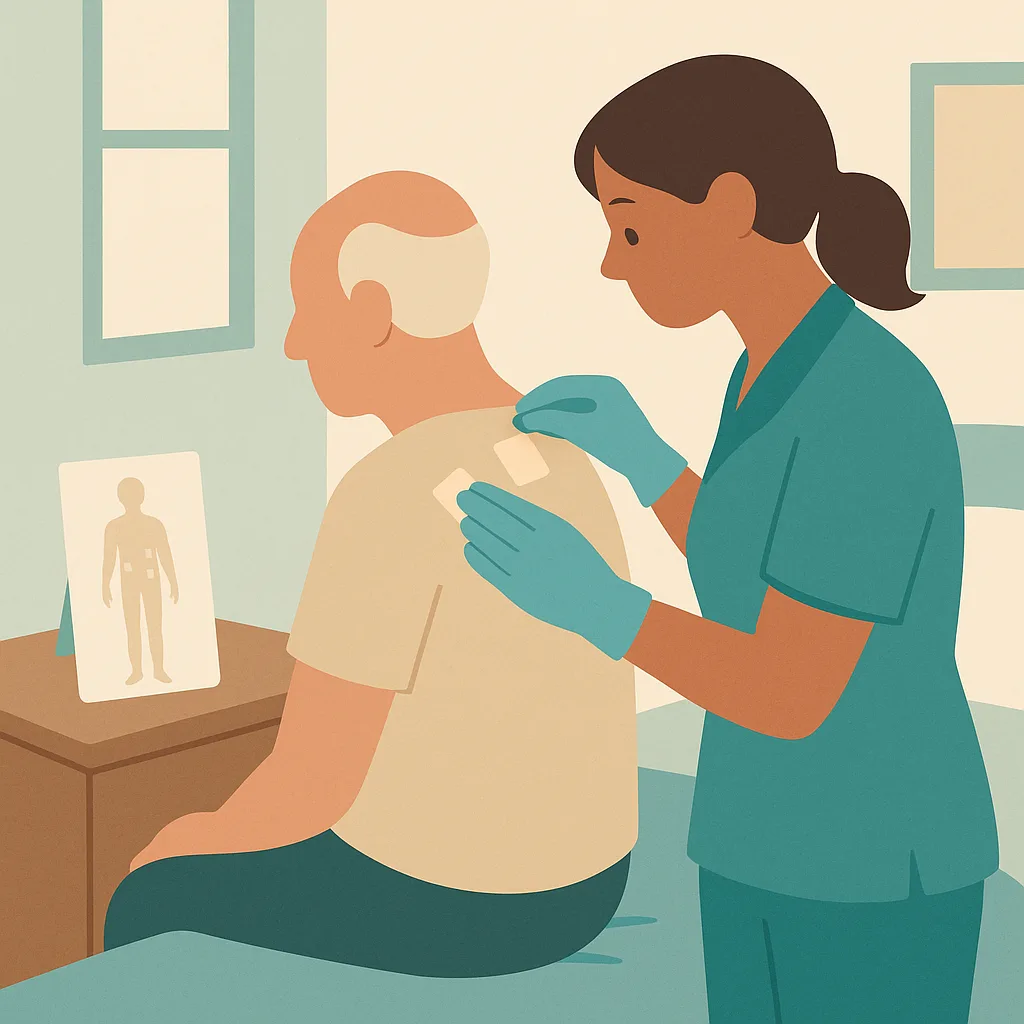
Give each medicine by the route and method prescribed, and as the pharmacy label directs. Support the person to sit upright for oral medicines, and offer a full glass of water unless their fluids are thickened, in which case follow their speech and language therapy plan. Do not touch tablets with bare hands: pop them from the pack into a medicine pot or use a clean spoon. Give one medicine at a time if that helps the person, and stay with them until they have swallowed it. Liquids should be shaken if the label says so and measured accurately with an oral syringe or medicine measure at eye level, never a household spoon. Do not crush tablets or open capsules unless a pharmacist has confirmed it is safe and it is recorded, because this can make medicines dangerous or ineffective. Creams and ointments are applied with gloves, to the area and in the amount shown on a body map or topical MAR. Some creams, including paraffin based emollients, soak into clothing and bedding and make them more flammable, so follow your fire safety advice for people using them. Patches, such as pain relief patches containing fentanyl or buprenorphine, must be applied at the right frequency and to a different site each time, as the label says. Remove the old patch before applying the new one and fold it sticky sides together for disposal, record the site, and never apply heat, such as a hot water bottle, over a patch, because it can release too much medicine. Inhalers should be used with the technique the person has been shown, often with a spacer; check with the pharmacist or nurse if you are unsure. Eye drops are given into the lower eyelid without the dropper touching the eye, with a gap of about five minutes between different drops. When required (PRN) medicines are given only when needed, following the person's PRN protocol, which says what the medicine is for, the signs to look for, the dose, minimum time between doses and the maximum in 24 hours. Record the reason and check and record whether it worked.
Recording and monitoring
The medicines administration record (MAR) is a legal record of the medicines given. Sign it immediately after the person has taken the medicine, never in advance and never for someone else. If a medicine is not given, use the correct code, such as refused, asleep, in hospital or not required, and explain in the notes. Leaving a gap is unsafe, because nobody can tell whether the dose was given. Electronic MAR systems work the same way: record at the time, as you give it. Only authorised, trained staff should make handwritten changes to a MAR, following your policy, for example when a prescriber changes a dose, and changes are usually checked by a second person. Never cross out or use correction fluid; errors are corrected so the original is still visible. Monitoring is part of administering. Watch for the effects a medicine should have, such as pain relief, and for side effects, such as drowsiness, dizziness, confusion, falls, constipation, rashes, bruising or bleeding. Some medicines need specific checks, such as blood sugar for people on insulin, or pulse before some heart medicines, but only carry these out if you are trained and it is in the person's plan. Report changes promptly, and record them. Medicines need regular review by the prescriber or pharmacist, including structured medication reviews, especially for people on many medicines or on antipsychotics for dementia, which should be reviewed regularly. Your observations inform these reviews. Moving between services is a risky time. When a person moves into care or returns from hospital, their medicines must be checked against the discharge information and their GP record, which is called medicines reconciliation. Send a current MAR and medicines information with anyone going into hospital.

Controlled drugs, storage and disposal
Controlled drugs are medicines that could be misused, such as morphine, oxycodone, fentanyl and methylphenidate. They are grouped into schedules. In care settings, unless a person is looking after their own medicines, Schedule 2 controlled drugs must be stored in a controlled drugs cupboard that meets legal requirements, and every movement recorded in a controlled drugs register: a bound book with numbered pages. Entries record receipt, administration, disposal and transfer, are made on the same day, and must not be crossed out or altered; corrections are signed and dated in the margin. Whenever possible, the member of staff giving a controlled drug is witnessed by a suitably trained colleague, who also signs the register. Stock is counted and checked regularly. Report any discrepancy immediately. In people's own homes, controlled drugs belong to the person and are usually stored in their home as agreed in their risk assessment, but you still record administration on the MAR and follow your employer's controlled drugs procedure. All medicines must be stored securely: in a locked trolley, cupboard or room, with keys kept by an authorised person and never left in the lock. Medicine trolleys are locked and secured when not in use and never left unattended. Store medicines at the temperature on the label. Most are kept below 25°C; medicines that need refrigeration are kept in a dedicated medicines fridge between 2°C and 8°C, with the temperature checked and recorded daily and anything out of range reported. People who manage their own medicines should have a lockable place to keep them. Unwanted, out of date or discontinued medicines are separated from current stock, recorded, and returned for disposal in line with your policy. care settings without nursing return them, including controlled drugs, to the community pharmacy, recording controlled drugs in the register with a witness. Never put medicines in the bin, toilet or sink.

Errors, your limits and seeking advice
Medication errors include giving the wrong medicine, dose, route or time, giving a medicine to the wrong person, missing a dose, giving a medicine the person is allergic to, and recording errors. A near miss is an error caught before it reached the person. They happen in every service, and what matters is what you do next. If you make or discover an error, make sure the person is safe first. Check them, and seek clinical advice straight away from the GP, NHS 111 or the pharmacist, or call 999 if they are unwell. Tell the senior or manager immediately. Record what happened, when, and what was done. Do not hide an error or wait to see if the person is affected. Your employer will inform the person or their family in line with the duty of candour, may need to notify CQC or the local safeguarding team, and will look at why it happened so it can be prevented. Being open is protected; covering up is not. Know the limits of your role. Only carry out medicines tasks you have been trained and assessed as able to do, for that person, as their plan and your policy say. Some tasks need specific training and delegation from a healthcare professional, such as insulin injections, buccal midazolam for seizures, PEG administration or rectal medicines. Never give medicines prescribed for someone else, never take verbal instructions to change a dose unless your policy allows and it is properly recorded, and never give a homely remedy outside the agreed policy. Seek advice whenever you are unsure: from the senior, the pharmacist, the prescriber or NHS 111. The pharmacist is an excellent source of advice about how to give medicines, side effects and interactions. After you pass the assessment, your manager or a suitably trained assessor will observe you giving medicines against a 12 point checklist. Every point must be met. If any point is not met yet, you will be told which, given support and further learning on it, and observed again. Your certificate is issued once your manager records a full sign-off.

The things your team must remember.
- Follow the six rights: right person, medicine, dose, route, time and documentation
- Check identity, allergies and the pharmacy label against the MAR every time
- People have the right to refuse; covert administration only after a best interests decision and pharmacy advice
- Sign the MAR immediately after the medicine is taken, never before
- Follow the PRN protocol and record the reason and the effect
- Schedule 2 controlled drugs go in the controlled drugs cupboard and register, with a trained witness
- Report errors and near misses straight away: the person's safety comes first
Not a slideshow once a year. Training that sticks.
CareStream delivers medication administration and competency training in the hub your team already uses, grounded in best practice and your own policies, so it fits your care setting and not a generic template.
Short teaching sections and a real care scenario, then an assessment that checks understanding.
Staff complete it in over 60 languages, while your records stay in English.
A wrong answer triggers a short follow-up lesson and a fresh question, so the gap is closed.
Automatic reminders at 90, 30 and 7 days, with a live compliance dashboard.
From your dashboard to your team, in the CareStream hub.
Training is delivered in the hub each staff member logs into. You allocate the modules, they complete them in their own language, and you get the completion records and certificates for your CQC evidence, with any gaps closed by automatic follow up training.
Assign Medication Administration and Competency to each staff member in seconds. No course builder and no setup for each person.
Staff work through the module on any device, in over 60 languages, teaching then checking understanding. A wrong answer sends a short follow up lesson.
See live completion status and a certificate for every person, ready as evidence for CQC.
Any step, in their language, in one tap.
Care teams are diverse and training should not leave anyone behind. On any lesson or question, a staff member taps the language button and the whole step flips into the language they think in. They understand it properly, and your records stay in English.
- One tap flips any lesson or question into their language, instantly.
- Over 60 languages, with no setup and no separate versions to manage.
- Completions and certificates stay in English for your CQC evidence.
Try the language buttons in the preview above.
Built for real learning, not box ticking
Every CareStream course goes further than a lesson and a quiz. These features come as standard on every course, giving your staff a richer way to learn and giving you the evidence to prove it.
Every course is built on recognised UK guidance and cites its sources, from NICE and Skills for Care to the NHS and the legislation itself.
A plain English glossary of the technical terms in each course. A simple way to support every learner, including staff with English as a second language.
A quick knowledge check before the lesson is compared with the final assessment, so every certificate comes with evidence of how much the course actually taught.
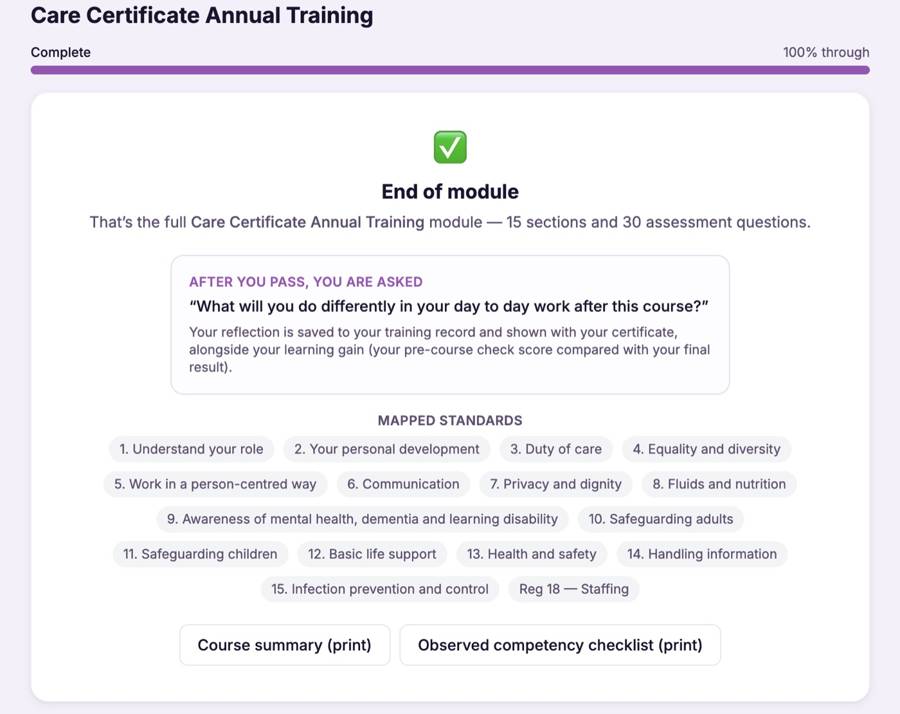
After passing, staff record what they will do differently in their day to day work. Their reflection is saved to their training record and shown with their certificate.

A printable one page takeaway of the outcomes, key points and key terms. Perfect for staff files, supervision conversations and the staff room wall.

A printable checklist for managers to confirm skills in practice, with a sign off section. It completes the picture beyond the knowledge assessment.
Wrong answers become lessons, not failures
Most e learning marks an answer wrong and moves on. CareStream does not. Every wrong answer triggers an automatic follow up loop that teaches the point again and rechecks it, so no knowledge gap is left behind.
A wrong answer immediately opens a short lesson explaining the point, so the gap is closed there and then.
A fresh question on the same point checks the lesson has landed. The loop repeats until it has.
Staff move on to the next module and their certificate once they genuinely know the answer, not just after one lucky guess.
Why choose CareStream?
Training built for the care sector, delivered the way busy teams actually learn.
- 90+ care-specific training courses
- Bitesize, engaging lessons your staff actually finish
- Mapped to the Care Certificate & CQC standards
- Available in 60+ languages
- Instant certificate on completion
- Flexible learning, anytime, on any device
- Content kept up to date with UK care regulations
- Time to complete: 1 hour
Frequently asked questions.
Is Medication Administration and Competency training mandatory in care settings?
How often should staff complete Medication Administration and Competency training?
Can CareStream deliver Medication Administration and Competency training in other languages?
Does the training include an assessment?
More CPD Certified training your team may need
Every course below is certified by The CPD Certification Service, delivered in the hub, in any language. Add any of these to your basket.
 One-off Certificate
Care Certificate
Annual refresher training across all 16 standards of the Care Certificate (March 2025). You will revisit every standard, from understanding your role and duty of care through person-centred working, communication, safeguarding, basic life support, health and safety, handling information and infection prevention and control, including the new standard on awareness of learning disability and autism. Each standard has a short lesson, a workplace scenario and a knowledge check, followed by a final assessment. Your knowledge certificate is issued once you pass the assessment and your manager has verified your observed competency assessment.
Bulk discounts from 10+ licences
 Annual Certificate
Food Hygiene
Annual food hygiene refresher for care workers who prepare, handle or serve food, or support people to eat and drink, in any adult social care setting. Built on the Skills for Care statutory and mandatory training guide and Food Standards Agency guidance for care homes, it covers why food safety matters, personal hygiene and fitness to work, chilling, cooking and reheating, cross contamination, cleaning, the 14 allergens, texture modified diets, gift food, and recording and reporting. Eight lessons with scenarios and activities, then a final assessment.
Bulk discounts from 10+ licences
 Annual Certificate
Infection Prevention and Control
Annual infection prevention and control refresher for care workers in residential, nursing, home care, supported living and day services. Built on the Skills for Care statutory and mandatory training guide, NHS England's national infection prevention and control manual and the adult social care IPC resource, it covers the chain of infection, standard precautions and your role, hand hygiene, PPE, recognising and reporting infection, outbreaks, cleaning, laundry and spills, waste, sharps and exposure incidents. Eight lessons with scenarios and activities, then a final assessment.
Bulk discounts from 10+ licences
 Annual Certificate
Moving and Handling of People
Annual moving and handling of people refresher for care workers who assist and move people in care homes, nursing homes, home care and supported living. Built on the Skills for Care statutory and mandatory training guide and Health and Safety Executive guidance, it covers the law, how backs are injured, risk assessment, safe handling principles, moving and positioning with dignity, hoists and slings, other equipment and falls, and the limits of your role. Eight lessons with scenarios and activities, a final assessment, then an observed practical assessment by your employer.
Bulk discounts from 10+ licences
 Annual Certificate
COSHH (Control of Substances Hazardous to Health)
Annual COSHH training for care, domestic, laundry, kitchen and maintenance staff in any adult social care setting. Built on the Control of Substances Hazardous to Health Regulations 2002 and Health and Safety Executive guidance, it covers what counts as a hazardous substance, how harm happens, hazard pictograms and safety data sheets, COSHH assessments and controls, safe use and storage, gloves and skin care, body fluids and medicines, and dealing with spills and exposure. Eight lessons with scenarios and activities, then a final assessment.
Bulk discounts from 10+ licences
 Annual Certificate
End of Life / Palliative Care
End of life and palliative care for care workers in care homes, nursing homes, home care and supported living, mapped to Tier 2 of the End of Life Care Core Skills Education and Training Framework and NICE guidance. It covers person centred end of life care, communication, advance care planning and the law, recognising the last days of life, symptoms and comfort, emotional, spiritual and cultural needs, supporting families and bereavement, and care after death and your own wellbeing. Eight lessons with scenarios and activities, then a final assessment.
Bulk discounts from 10+ licences
 Annual Certificate
GDPR / Data Protection
Annual data protection and data security refresher for everyone working in adult social care, meeting the Data Security and Protection Toolkit expectation of yearly staff training. Built on UK GDPR, the Data Protection Act 2018 as amended in 2025, ICO guidance and the Caldicott Principles, it covers the data protection principles, confidentiality and lawful sharing, people's rights, recording and storing information, cyber threats and scams, paper records and devices, and recognising and reporting data breaches. Eight lessons with scenarios and activities, then a final assessment.
Bulk discounts from 10+ licences
 Annual Certificate
General Health & Safety Awareness
Annual health and safety refresher for everyone working in adult social care, in care homes, people's own homes, supported living and day services. Built on the Skills for Care statutory and mandatory training guide and Health and Safety Executive guidance for health and social care, it covers your legal duties, risk assessment, common hazards in care, hazardous substances, security and lone working, work related stress and your own wellbeing, responding to accidents and sudden illness, and reporting. Eight lessons with scenarios and activities, then a final assessment.
Bulk discounts from 10+ licences
 Annual Certificate
Mental Health Awareness
Mental health awareness for everyone working in adult social care, mapped to Tier 1 of the Mental Health Core Capabilities Framework (2026). It covers what mental health and wellbeing mean, common mental health needs, stigma, rights and trauma informed practice, communicating with people in distress, physical health and loneliness, older people and people with a learning disability or who are neurodivergent, recognising and responding to self harm and suicide, and working with families, other services and the law. Eight lessons with scenarios and activities, then a final assessment.
Bulk discounts from 10+ licences
Give your team medication administration and competency training that actually sticks.
Buy your licences, allocate them in seconds, and let the evidence build itself.
Compared
Three ways to train a care team.
These modules are written and kept current by us, so your managers do not have to write or maintain them. We have compared what each approach does rather than naming providers, because products change and this should still be true next year.
| CareStream | A generic e-learning library | A trainer you book | |
|---|---|---|---|
| Try a real lesson and a real question before you buy | |||
| Learning outcomes and time to complete stated up front | |||
| Written lesson sections, each with its own illustration | |||
| Interactive exercises after the lesson that teaches them, in every module | |||
| Assessment in every module, with the key points to revisit | |||
| Taken in any of sixty plus languages | |||
| A wrong answer triggers a follow-up lesson, not just a re-sit | |||
| Practical sign-off by a manager where the subject needs it | |||
| Completion files itself into your training matrix and evidence pack | |||
| Bought one module at a time, with no annual contract |
Generic libraries are often cheaper per learner. They teach a national standard rather than being built, updated and evidenced around the way a CQC-registered service is actually inspected.
Care policies
Every module is written from a policy
If the policy behind it is out of date, the training inherits that. Sixty six policies written for your service, checked against current law and read by a person before they carry your name, from £39.




